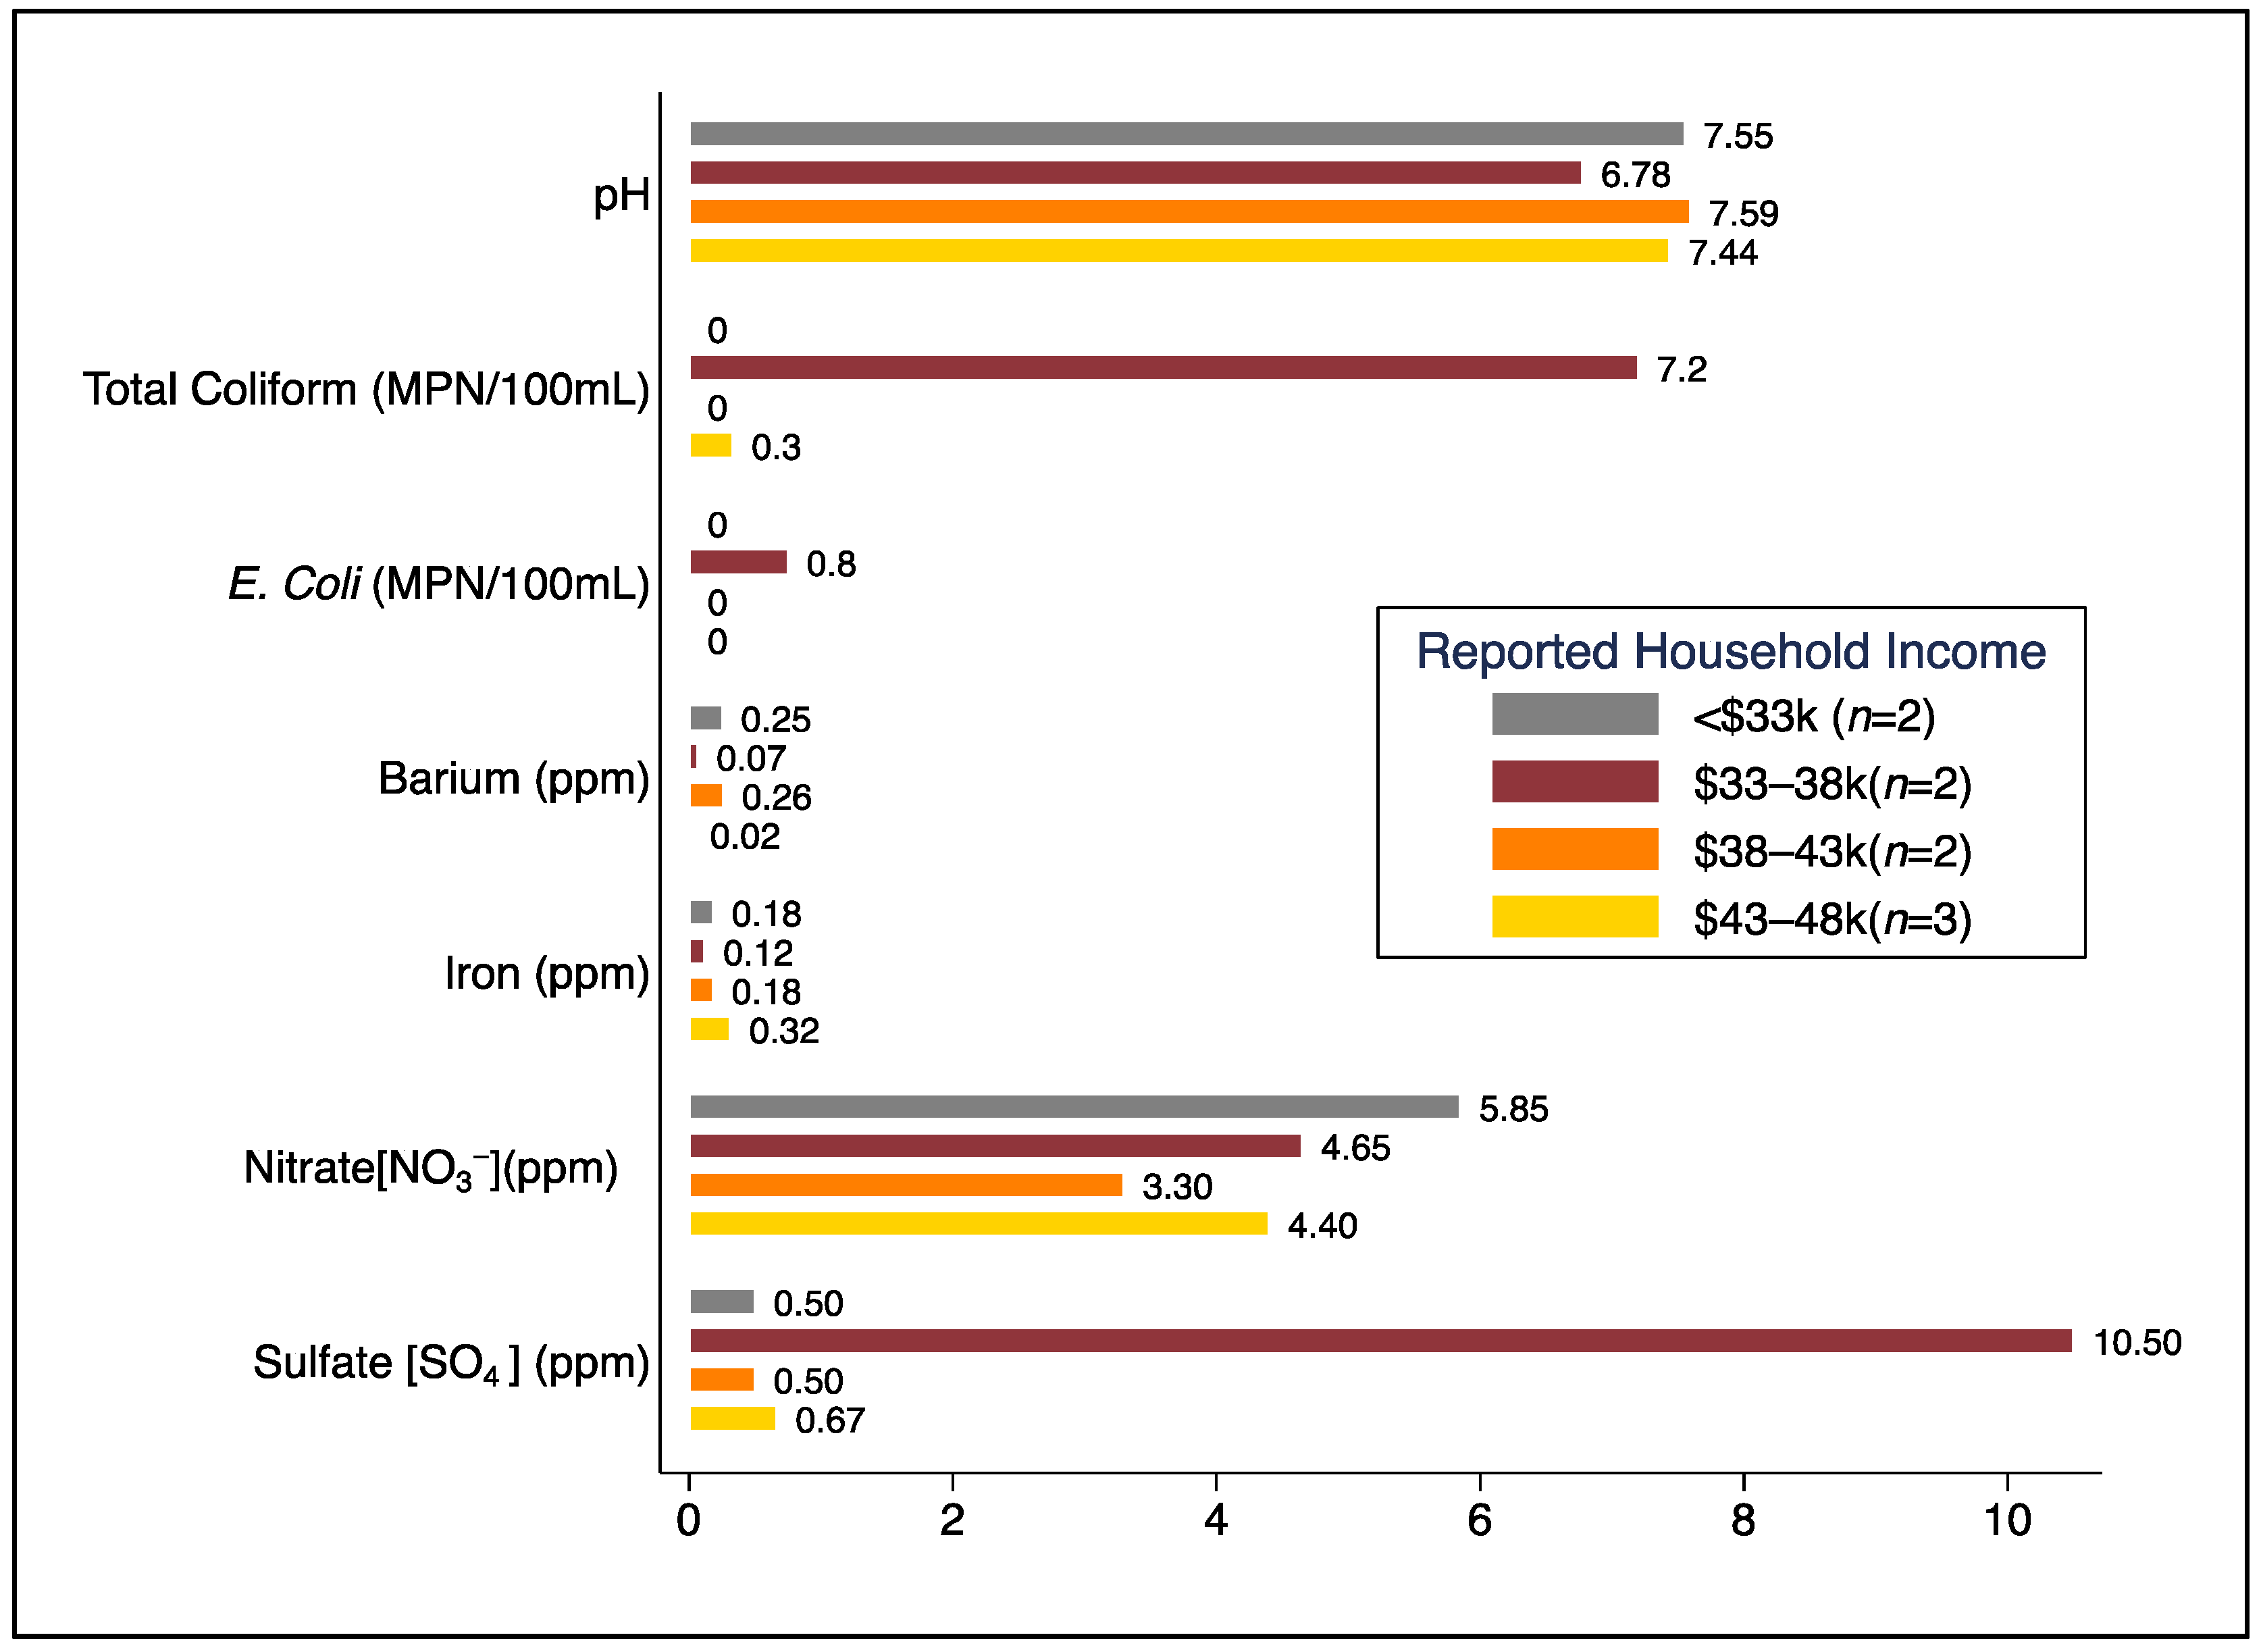Themes / Topics Drinking Water
-1
archive,tax-theme_topic,term-drinking-water,term-75,wp-theme-stockholm,stockholm-core-1.2.2,select-theme-ver-9.0,ajax_fade,page_not_loaded,,qode_menu_center,wpb-js-composer js-comp-ver-6.3.0,vc_responsive

Microbiological and Chemical Contaminants in Single-Use and Multipackage Bottled Water: Inter- and Intra-analyses of 26 Bottled Water Brands in the USA
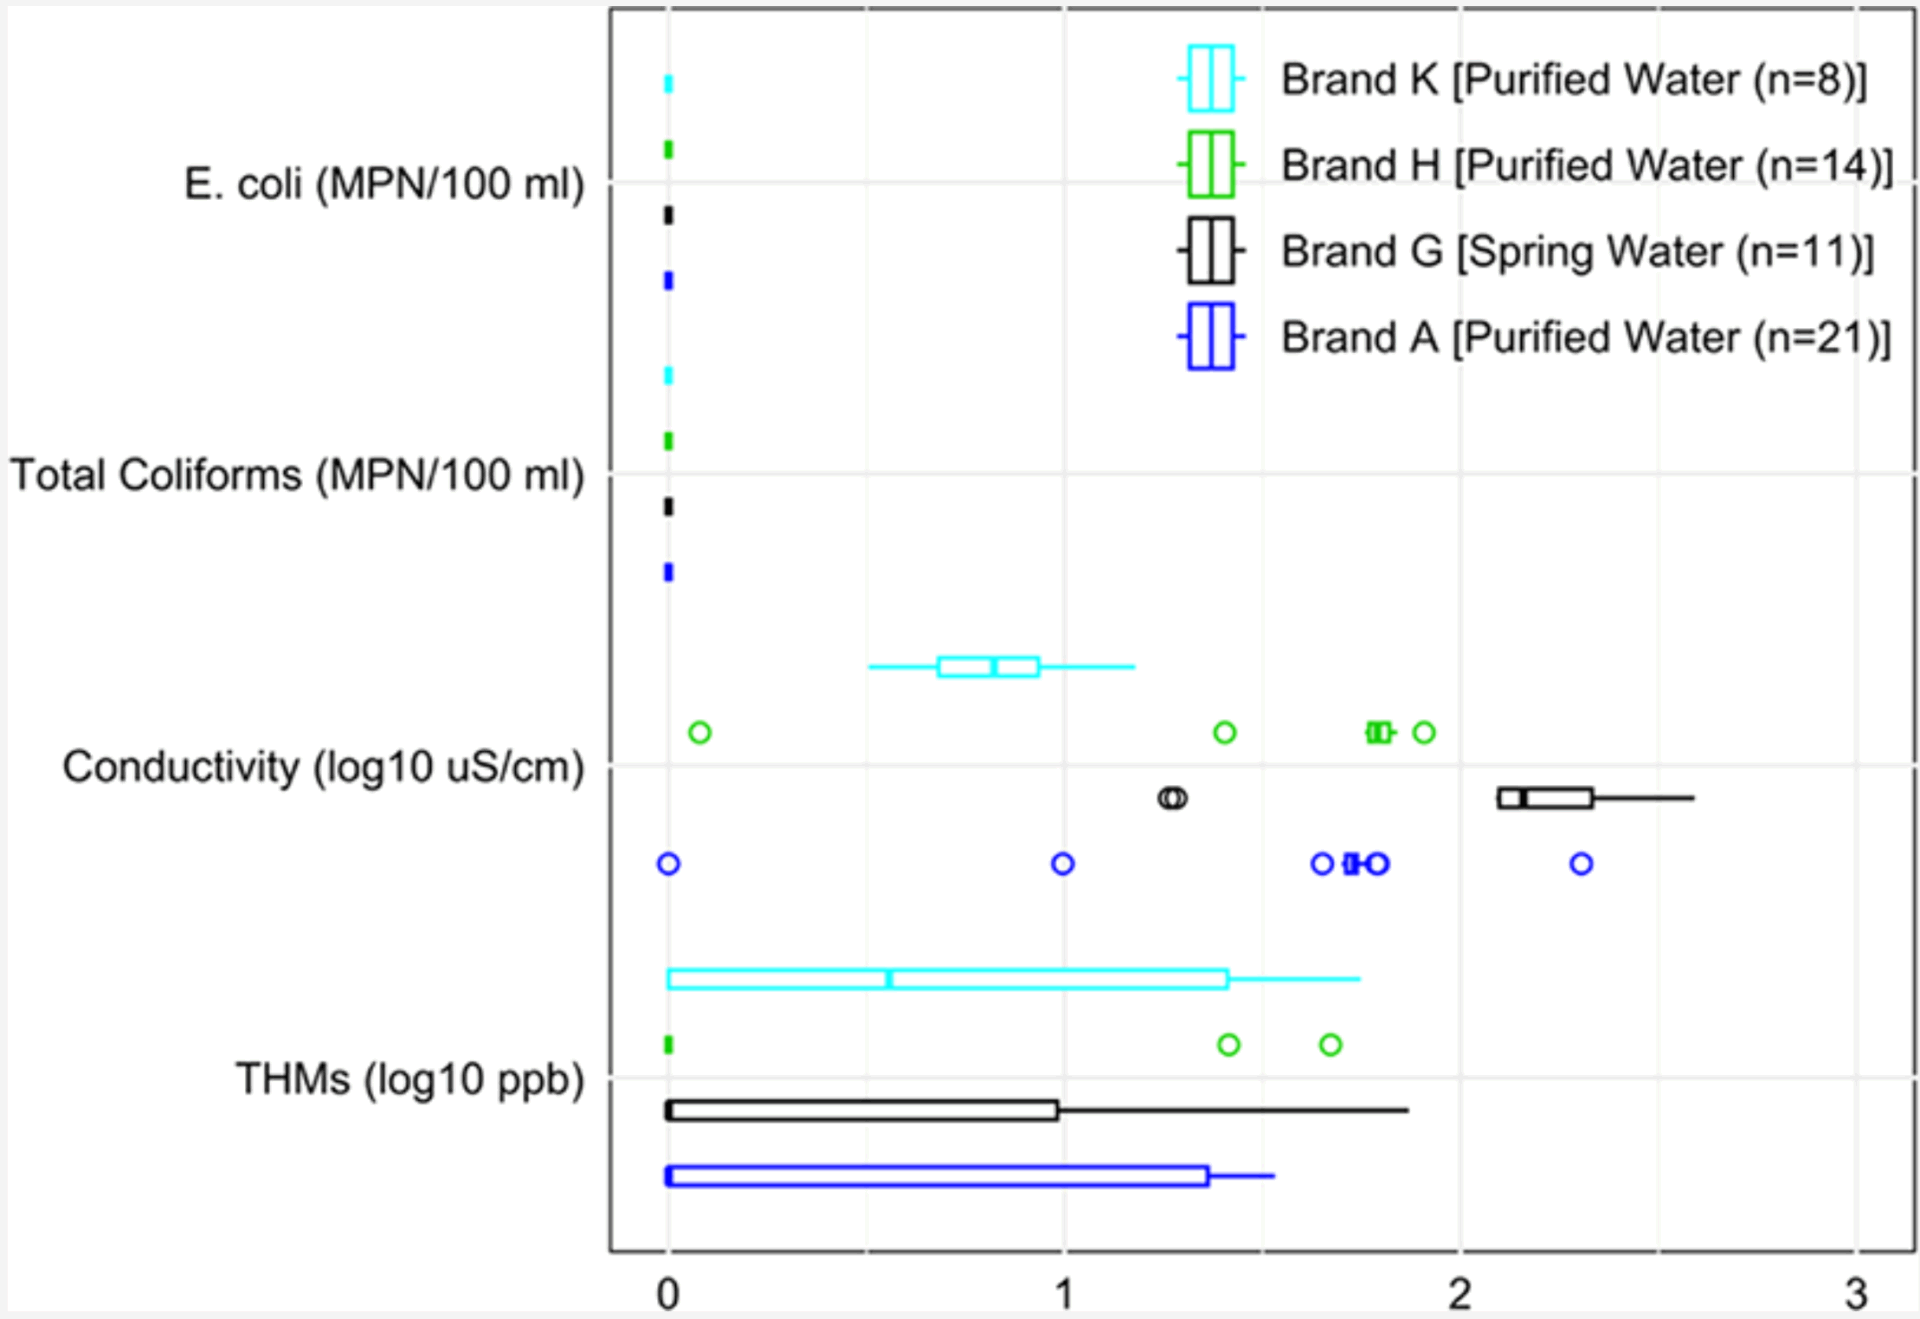
Relatively few published studies have assessed the microbiological or chemical quality of bottled water in the USA. We purchased all single and multipackage bottled water sold in grocery and retail stores in one county in Virginia. 107 samples, across 26 brands, were tested for pH, conductivity, dissolved oxygen, total coliform, E. coli, nitrate, sulfate, free chlorine, total trihalomethanes (THMs, a component of disinfection byproducts), fluoride, and heavy metals. 64.5% (n = 69) of samples were purified water and 35.5% (n = 38) were spring water. Contaminant concentrations were higher overall in spring water samples. Total coliforms and E. coli were not detected in any samples. 1.4% (n = 1) of purified bottled water samples exceeded regulatory standards for THM (80 ppb), and 7.2% (n = 5) and 10.5% (n = 4) of purified and spring samples exceeded 1/2 the THM standard, respectively. No spring water samples exceeded standards for heavy metals, but one purified bottled water sample exceeded the standard for cadmium. We observed considerable within-brand variability in concentrations for a number of parameters including THMs, calcium, silicon, and strontium. This is the first study we are aware of to analyze contaminant variability within bottled water brands. Our results indicate that monitoring and reporting requirements for bottled water should be improved.

The Rural Water & Health Study (RWELL)

Tens of millions of people in the USA live in homes with unregulated private wells, primarily in rural regions. However, our understanding of drinking water contaminants and associated health impacts for individuals living in households with private water supply in rural areas of the USA is highly limited. Our prior studies in Central Appalachia (described below), and studies led by our collaborators, indicate that many lower-income households in rural areas with private wells and spring water have relatively higher exposures to microbiological contaminants in their drinking water. The overarching goal of the RWELL Study is to assess the potential of a household-level water treatment intervention for further expanding safe water access and improving health outcomes and well-being for rural households without utility-supplied water. Funded by the NIH (1R01AI187428), the study is a collaborative effort between researchers at Virginia Tech (VT), East Tennessee State University (ETSU), the University of North Carolina, Chapel Hill, and the University of California, Berkeley. Starting in 2026, teams at VT and ETSU will begin staggered enrollment of households that use well water and spring water in regions of southwest Virginia and northeast Tennessee to conduct a cluster-randomized controlled trial to better understand sources of drinking water used, people’s opinions about their water sources, water use and quality, health issues, and, ultimately, to evaluate hypothesized benefits of point-of-use water filtration. It is hoped that results from this study will also help to increase awareness of the need for improved policies and programs to further expand access to safe drinking water for households in rural Appalachia, as well as other rural areas of the USA and beyond.

Point-of-use chlorine residuals and disinfection byproduct occurrences in rural households served by public water utilities in Appalachian Virginia

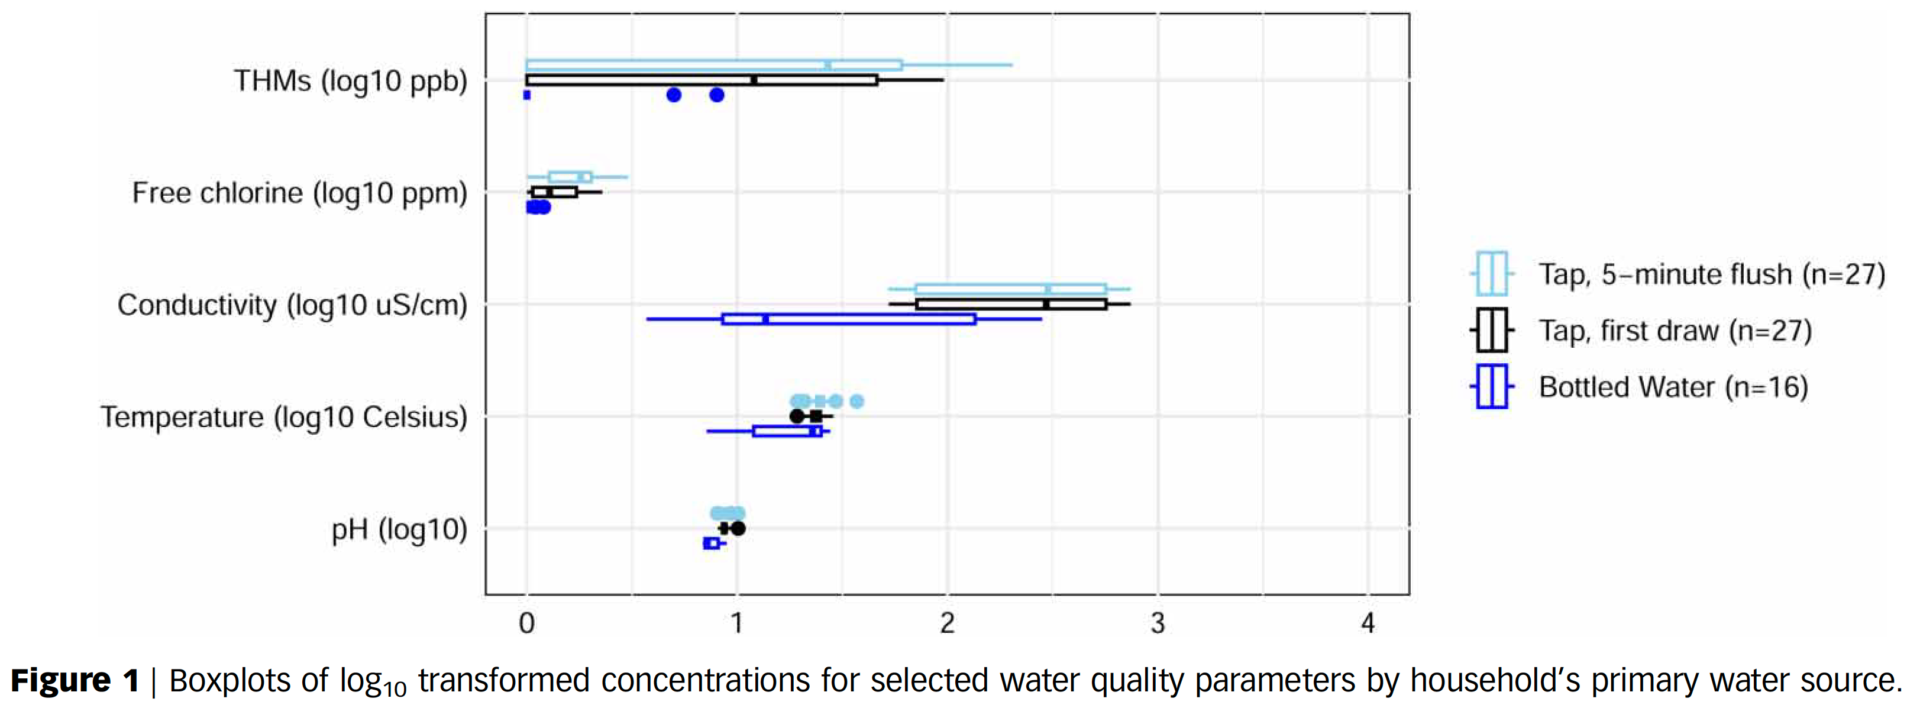
Abstract/Summary: We characterized concentrations of trihalomethanes (THMs), a measure of disinfection byproducts (DBPs), in tap water samples collected from households with utility-supplied water in two rural counties in Appalachian Virginia, and assessed associations with pH, free chlorine, and metal ions which can impact THM formation. Free chlorine concentrations in all samples (n = 27 homes) complied with EPA drinking water guidelines, though 7% (n = 2) of first draw samples and 11% (n = 3) of 5-min flushed-tap water samples exceeded the US Safe Drinking Water Act (SDWA) maximum contaminant level (MCL) for THM (80 ppb). Regression analyses showed that free chlorine and pH were positively associated with the formation of THM levels above SDWA MCLs (OR = 1.04, p = 0.97 and OR = 1.74, p = 0.79, respectively), while temperature was negatively associated (OR = 0.78, p = 0.38). Of the eight utilities serving study households, samples from water served by three different utilities exceeded the EPA MCL for THM. Overall, these findings do not indicate substantial exposures to DBPs for rural households with utility-supplied water in this region of southwest Virginia. However, given the observed variability in THM concentrations between and across utilities, and established adverse health impacts associated with chronic and acute DBP exposure, more research on DBPs in rural Central Appalachia is warranted.

Drinking water sources, quality, and associated health outcomes in Appalachian Virginia: A risk characterization study in two counties

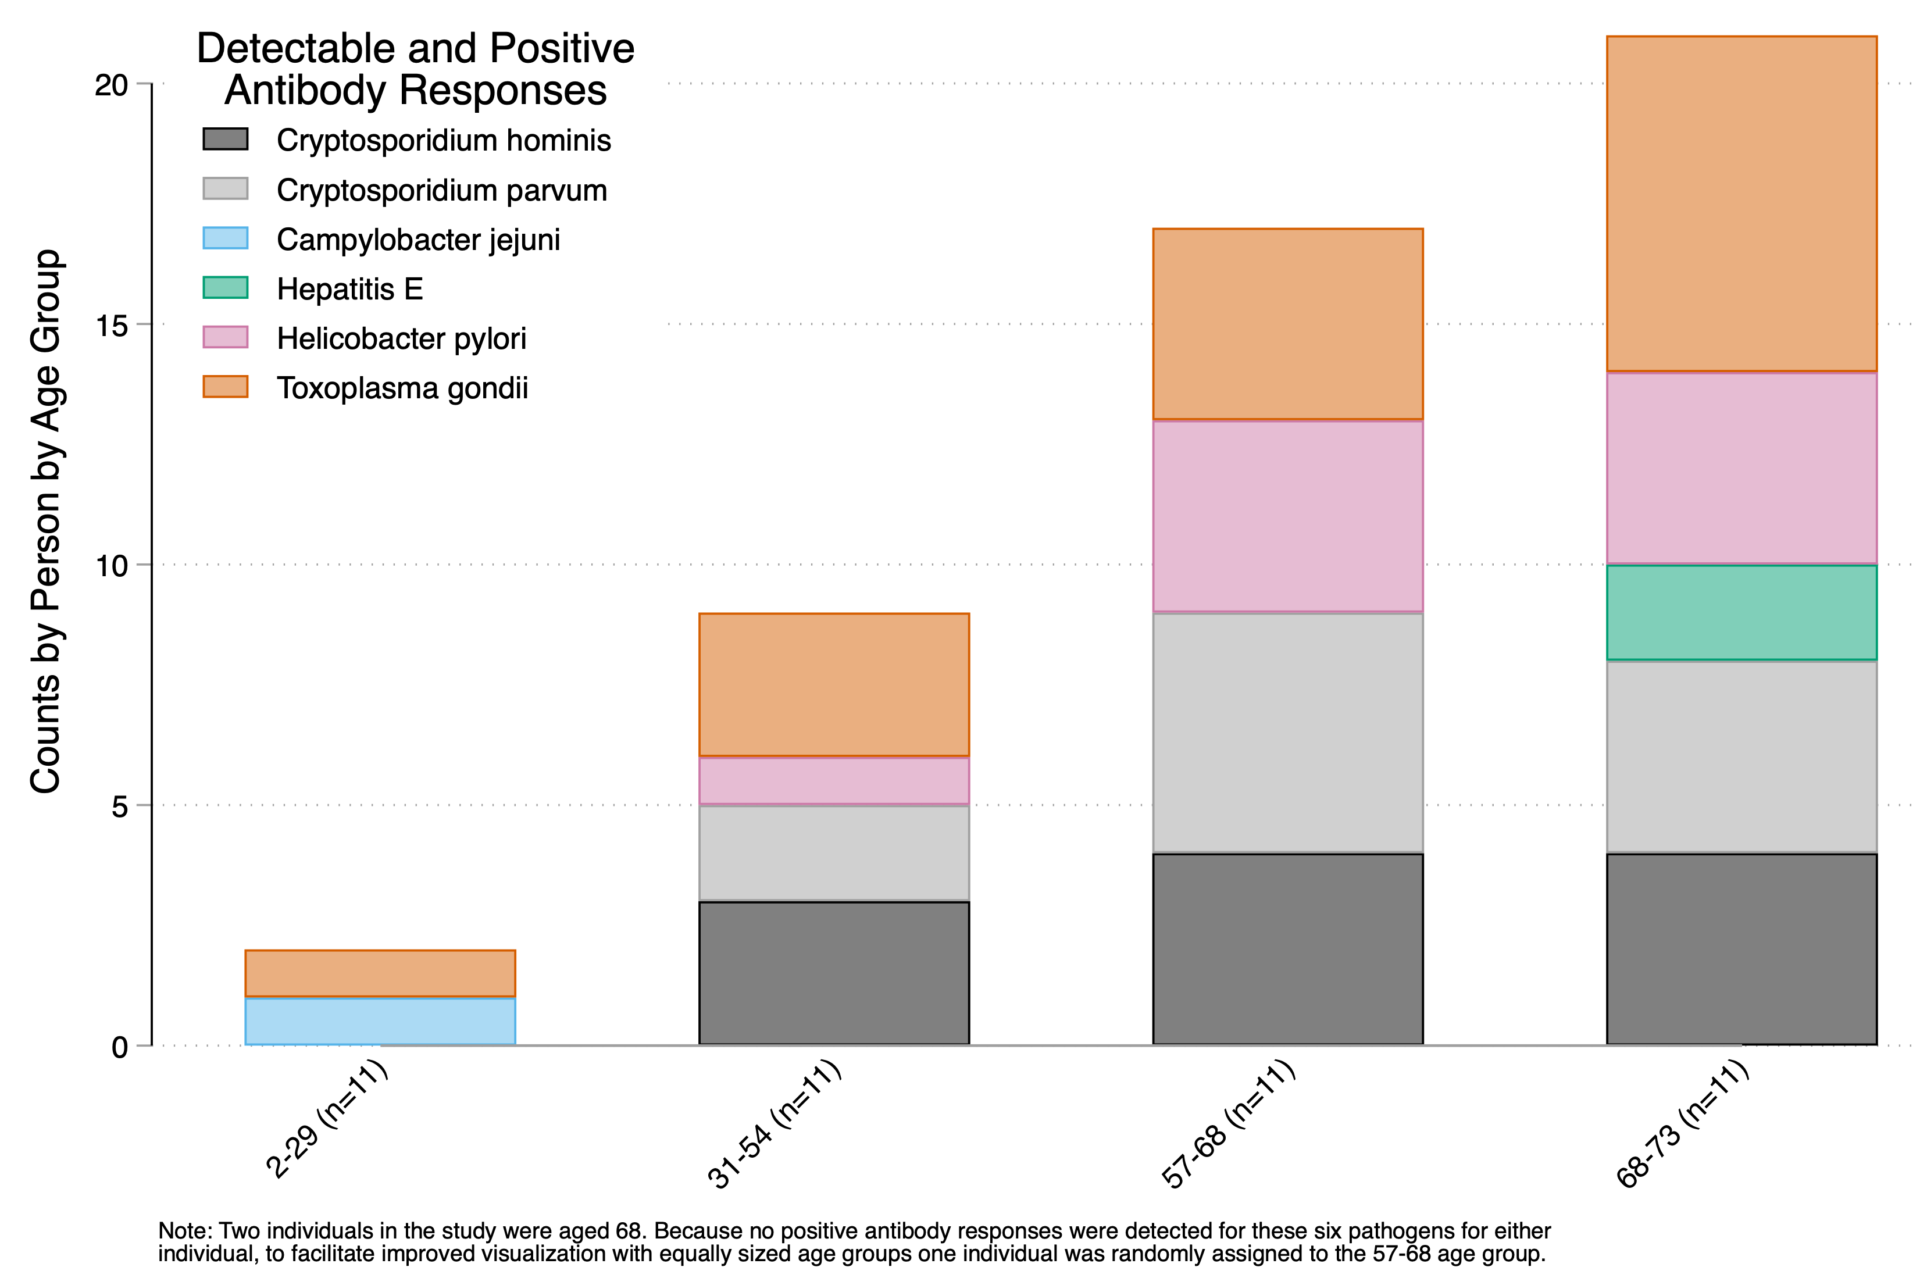
Abstract/Summary: In the US, violations of drinking water regulations are highest in lower-income rural areas overall, and particularly in Central Appalachia. However, data on drinking water use, quality, and associated health outcomes in rural Appalachia are limited. We sought to assess public and private drinking water sources and associated risk factors for waterborne pathogen exposures for individuals living in rural regions of Appalachian Virginia. We administered surveys and collected tap water, bottled water, and saliva samples in lower-income households in two adjacent rural counties in southwest Virginia (bordering Kentucky and Tennessee). Water samples were tested for pH, temperature, conductivity, total coliforms, E. coli, free chlorine, nitrate, fluoride, heavy metals, and specific pathogen targets. Saliva samples were analyzed for antibody responses to potentially waterborne infections. We also shared water analysis results with households. We enrolled 33 households (83 individuals), 82% (n = 27) with utility-supplied water and 18% with private wells (n = 3) or springs (n = 3). 58% (n = 19) reported household incomes of <$20,000/year. Total coliforms were detected in water samples from 33% (n = 11) of homes, E. coli in 12%, all with wells or springs (n = 4), and Aeromonas, Campylobacter, and Enterobacter in 9%, all spring water (n = 3). Diarrhea was reported for 10% of individuals (n = 8), but was not associated with E. coli detection. 34% (n = 15) of saliva samples had detectable antibody responses for Cryptosporidium spp., C. jejuni, and Hepatitis E. After controlling for covariates and clustering, individuals in households with septic systems and straight pipes had significantly higher likelihoods of antibody detection (risk ratios = 3.28, 95%CI = 1.01–10.65). To our knowledge, this is the first study to collect and analyze drinking water samples, saliva samples, and reported health outcome data from low-income households in Central Appalachia. Our findings indicate that utility-supplied water in this region was generally safe, and individuals in low-income households without utility-supplied water or sewerage have higher exposures to waterborne pathogens.

Microbiological and chemical drinking water contaminants and associated health outcomes in rural Appalachia, USA: A systematic review and meta-analysis

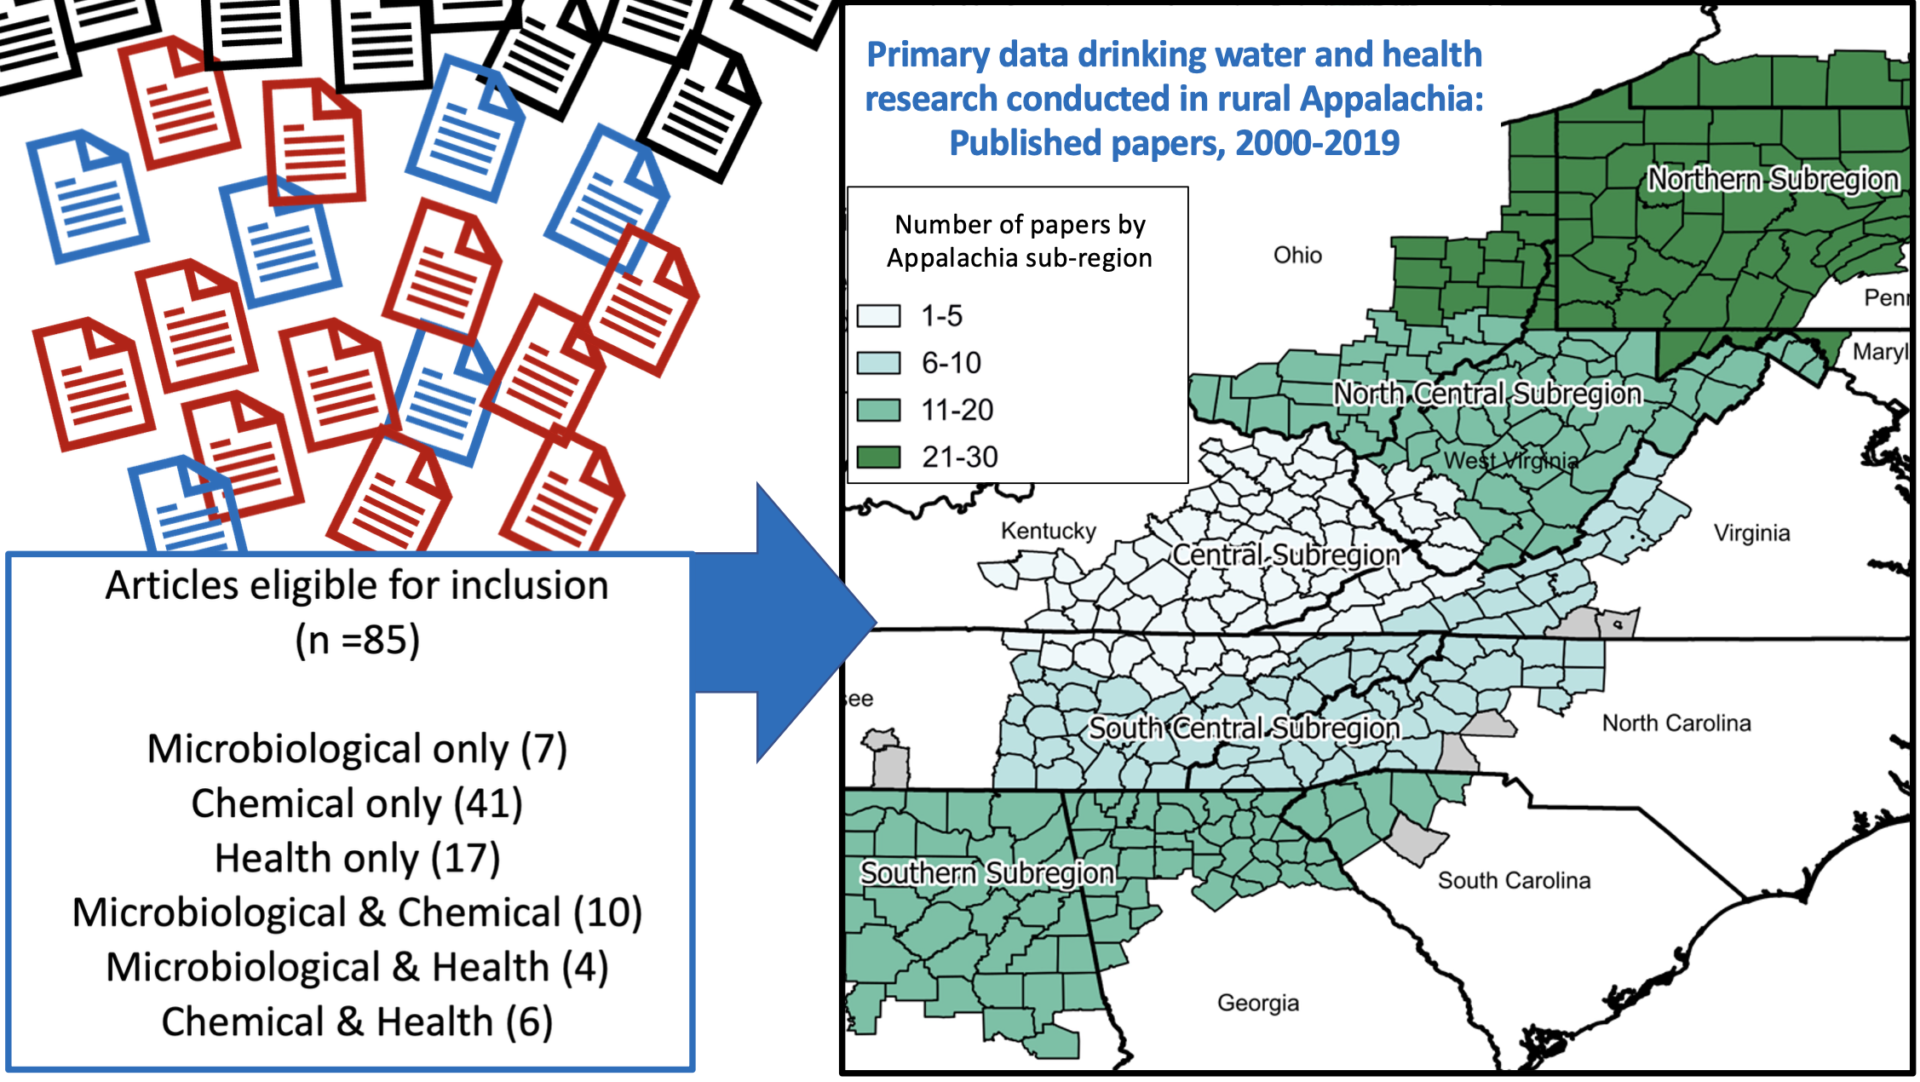
Abstract/Summary: In rural areas of the United States, an estimated ~1.8 million people lack reliable access to safe drinking water. Considering the relative dearth of information on water contamination and health outcomes in Appalachia, we conducted a systematic review of primary data studies published from 2000-2019. Of the 3,452 records identified for screening, 85 met our eligibility criteria. Most studies were conducted in Northern (32%, n=27) and North Central (24%, n=20) Appalachia, and only 6% (n=5) in Central Appalachia. Across studies, E. coli were detected in 10.6% of samples. 32% (n=27) of studies assessed health outcomes, but only 4.7% (n=4) used case-control or cohort designs (all others were cross-sectional). The most commonly reported outcomes were detection of PFAS in blood serum (n=13), gastrointestinal illness (n=5), and cardiovascular-related outcomes (n=4). Overall, based on the number and quality of eligible studies identified, we could not reach clear conclusions about the state of water quality, or its impacts on health, in any of Appalachia’s subregions. More epidemiologic research is needed to understand contaminated water sources, exposures, and potentially associated health outcomes in Appalachia.

Drinking Water & Health in Rural Appalachia

We are working on a number of projects to better understand issues related to drinking water (access, quality, use), sanitation, and reported and measured health outcomes in the Appalachia region, with a focus on children and adults living in Central Appalachia. In 2020, we started a comprehensive systematic review and meta-analysis study to identify and synthesize published research on drinking water contamination and associated health outcomes in the Appalachian region over a 20-year time period. We pre-registered our study protocols, completed data extraction and analysis in 2022, and published our findings in 2023 – the limited number and nature of the studies identified demonstrated that more epidemiologic research is needed to understand exposures to drinking water contaminants in this region. From 2021 to 2023, in collaboration with UVA, ETSU, a regional non-profit, a local utility, and others, we conducted a water-and-health focused cross-sectional study and a prospective cohort study in southwest VA (an important component of these studies is that we also share water testing results with participating households). In 2022, we published findings from the cross-sectional study (a small community of households with private wells), and we published baseline findings from the cohort study (rural households with utility-supplied and private well and spring water in two counties) in 2024. Given the relatively high rates of bottled water use/reliance we observed in rural households, we also conducted a study to analyze the quality of bottled water sold in the region; we published those bottled water findings in 2024. Building on findings from these studies, we conducted two well water and spring water focused studies: a 2024-2025 cross-sectional study in VA, and – in collaboration with ETSU, a regional non-profit, scientists at EPA, and others – we conducted a 2023/24-2025 prospective safe water intervention pilot study in rural regions of VA and TN (and anticipate publishing results in late 2026/2027). These studies and associated findings informed the design of the RWELL Study, described above.

The Human Right to Water: A 20-Year Comparative Analysis of Arsenic in Rural and Carceral Drinking Water Systems in California

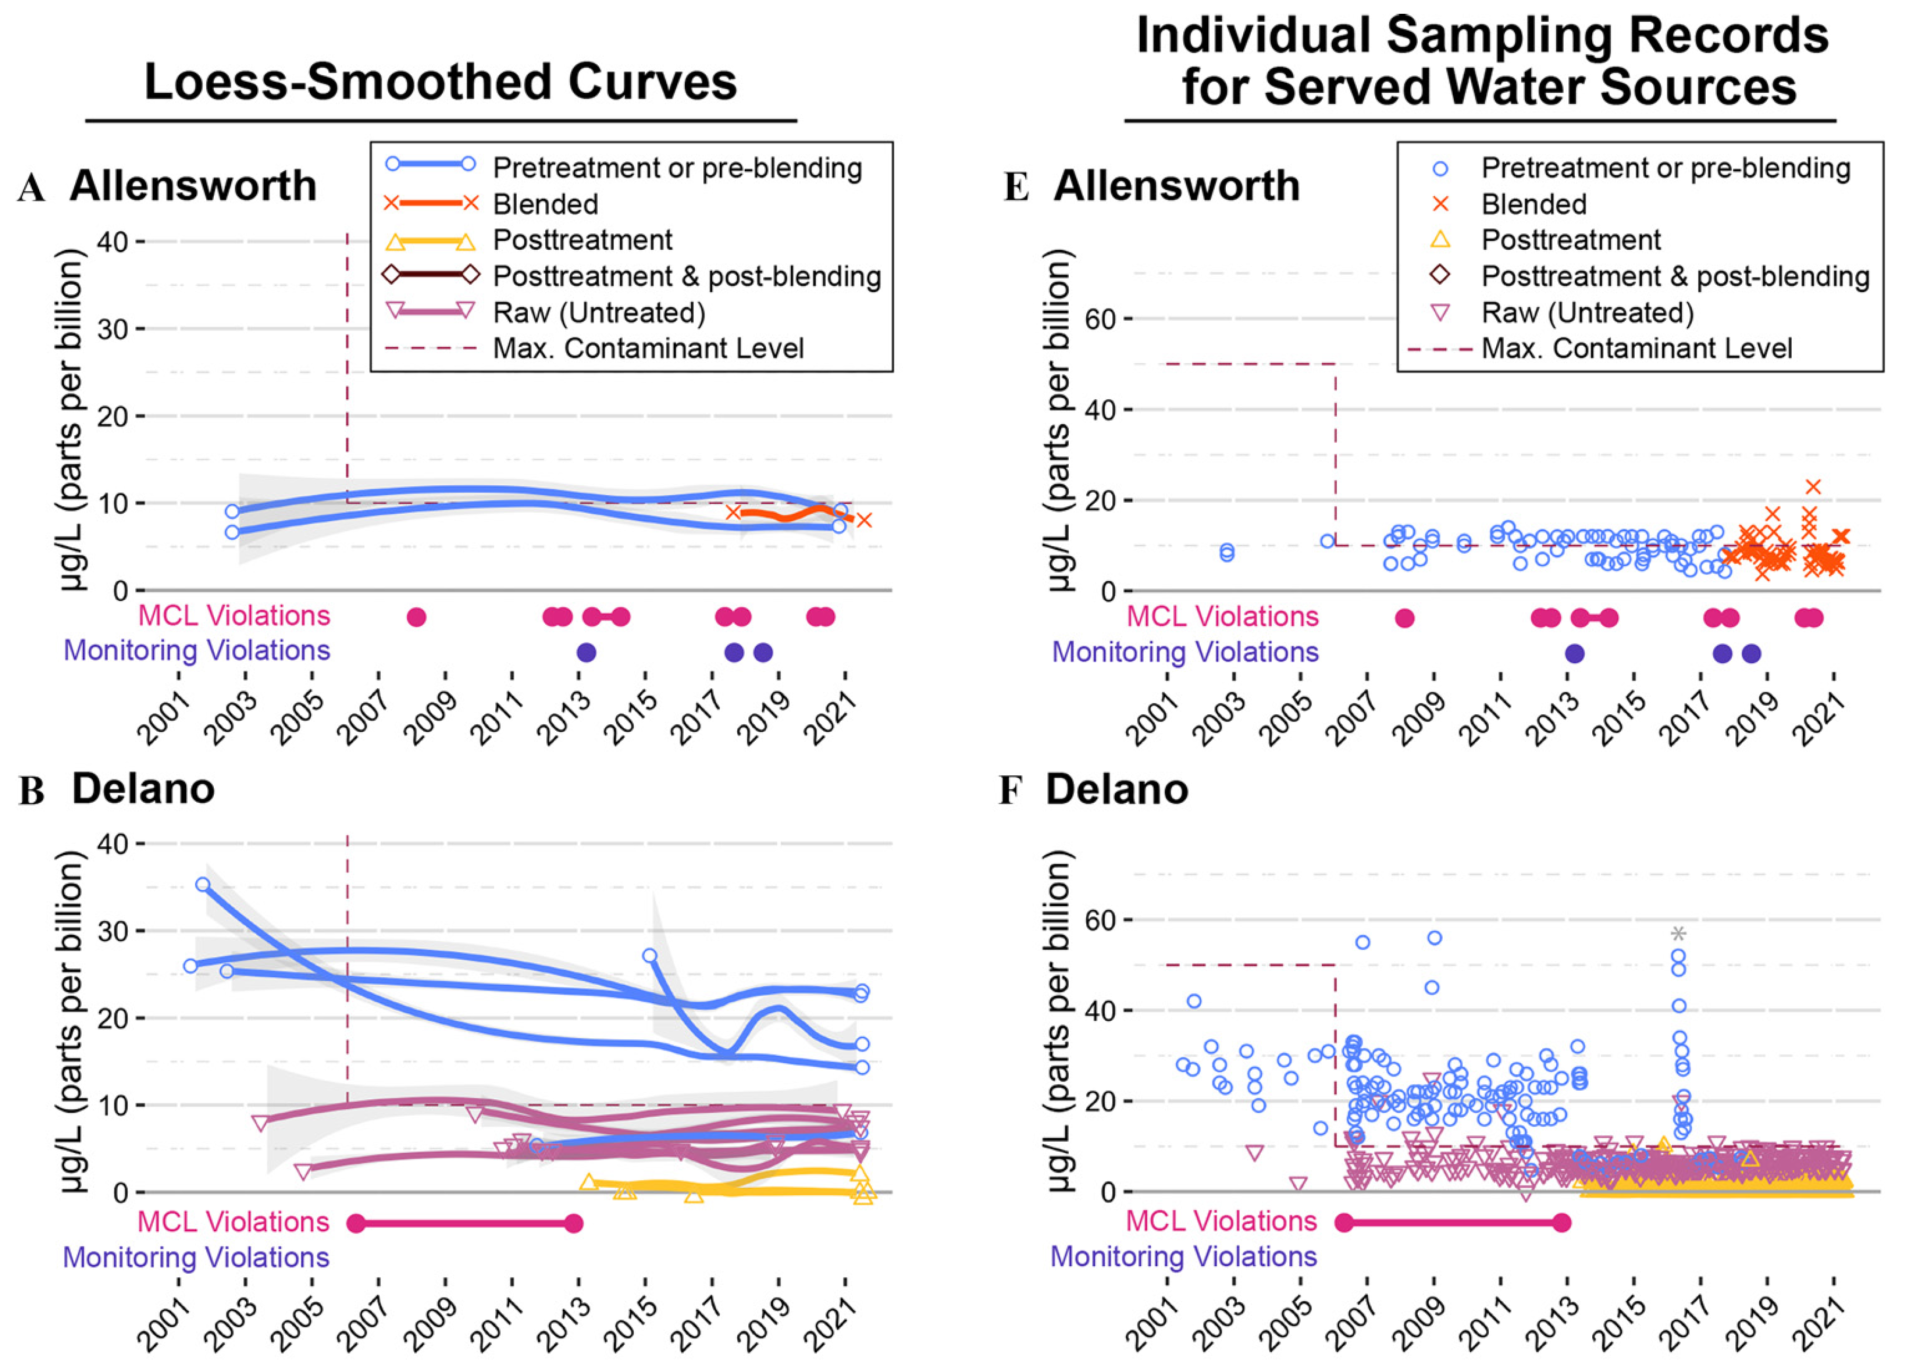
Abstract/Summary: Access to safe drinking water is considered a universal human right. In the U.S., exposure to arsenic contamination in drinking water disproportionately impacts small, groundwater-reliant communities and communities of color. Limited research exists on water quality in prisons; however, prisons in the Southwestern U.S. have elevated arsenic concentrations compared to other community water systems (CWS) in the region. In this paper we present a comparative analysis of 20 years of data (2001-2021) on arsenic concentrations in the CWSs serving Kern Valley State Prison (KVSP) and three neighboring rural communities: Allensworth, Delano, and McFarland. Our objective was to better understand trends in water quality, compliance, and treatment following adoption of the revised arsenic MCL, and to elucidate differences, if any, between neighboring incarcerated and non-incarcerated populations.

Bottled and Well Water Quality in a Small Central Appalachian Community: Household-Level Analysis of Enteric Pathogens, Inorganic Chemicals, and Health Outcomes in Rural Southwest Virginia

Abstract/Summary: Consumption of unsafe drinking water is associated with a substantial burden of disease globally. In the US, ~1.8 million people in rural areas lack reliable access to safe drinking water. Our objective was to characterize and assess household-level water sources, water quality, and associated health outcomes in Central Appalachia. We collected survey data and water samples (tap, source, and bottled water) from consenting households in a small rural community without utility-supplied water in southwest Virginia. Water samples were analyzed for physicochemical parameters, total coliforms, E. coli, nitrate, sulfate, metals (e.g., arsenic, cadmium, lead), and 30+ enteric pathogens. Among the 69% (n = 9) of households that participated, all had piped well water, though 67% (n = 6) used bottled water as their primary drinking water source. Total coliforms were detected in water samples from 44.4% (n = 4) of homes, E. coli in one home, and enteric pathogens (Aeromonas, Campylobacter, Enterobacter) in 33% (n = 3) of homes. Tap water samples from 11% (n = 1) of homes exceeded the EPA MCL for nitrate, and 33% (n = 3) exceeded the EPA SMCL for iron. Among the 19 individuals residing in study households, reported diarrhea was 25% more likely in homes with measured E. coli and/or specific pathogens (risk ratio = 1.25, cluster-robust standard error = 1.64, p = 0.865). Although our sample size was small, our findings suggest that a considerable number of lower-income residents without utility-supplied water in rural areas of southwest Virginia may be exposed to microbiological and/or chemical contaminants in their water, and many, if not most, rely on bottled water as their primary source of drinking water.

Bottled water quality and associated health outcomes: A systematic review and meta-analysis of 20 years of published data from China

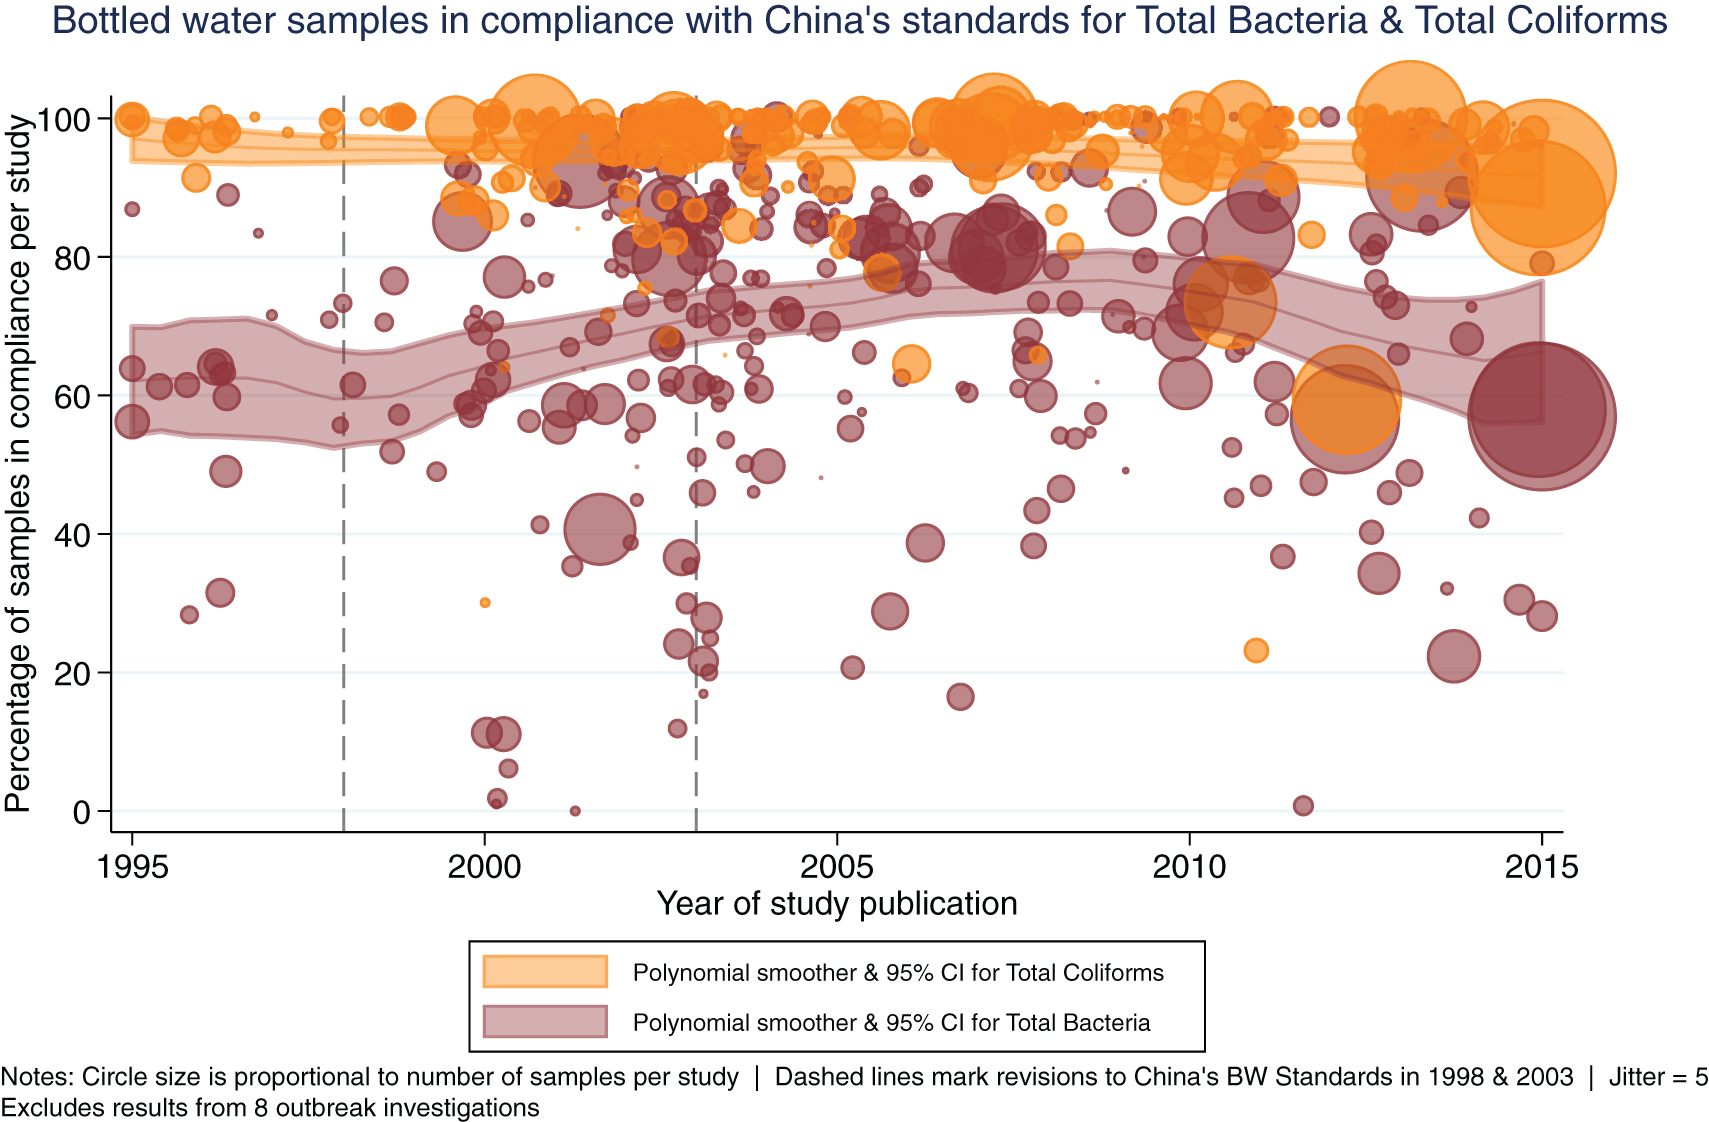
Abstract/Summary: Bottled water is a rapidly growing yet relatively understudied source of drinking water globally. In addition to concerns about the safety of bottled water, the adverse environmental health and social impacts associated with bottled water production, distribution, consumption, and reliance are considerable. Our objective was to comprehensively review, analyze, and synthesize ∼20 years of publicly available data on bottled water quality and associated health outcomes in China. We conducted a systematic review and meta-analysis of publicly available studies of bottled water quality and associated health outcomes in China published between 1995 and early 2016 (in Chinese and English). We pre-specified and registered our study protocol, independently replicated key analyses, and followed standardized reporting guidelines. Our search identified 7059 potentially eligible records. Following screening, after full-text review of 476 publications, 216 (reporting results from 625 studies) met our eligibility criteria. Among many findings, 93.7% (SD = 10.1) of 24 585 samples tested for total coliforms (n = 241 studies), and 92.6% (SD = 12.7) of 7261 samples tested for nitrites (n = 85 studies), were in compliance with China’s relevant bottled water standards. Of the studies reporting concentration data for lead (n = 8), arsenic (n = 5), cadmium (n = 3), and mercury (n = 3), median concentrations were within China’s standards for all but one study of cadmium. Only nine publications reported health outcome data, eight of which were outbreak investigations. Overall, we observed evidence of stable or increasing trends in the proportions of samples in compliance over the ∼20 year period; after controlling for other variables via meta-regression, the association was significant for microbiological but not chemical outcomes (p = 0.017 and p = 0.115, respectively). Bottled water is typically marketed as being safe, yet in most countries it is less well-regulated than utility-supplied drinking water. Given the trend of increasing bottled water use in China and globally—and the associated environmental health impacts—we hope this work will help to inform policies and regulations for improving bottled water safety, while further highlighting the need for substantially expanding the provision of safe and affordable utility-supplied drinking water globally.

Poverty, Water, Climate Change, & Health in Sub-Saharan Africa

As described below (see other project summaries), the Multidimensional Poverty Assessment Tool (MPAT) was created in two phases (from 2008 to 2014) via a collaborative, international initiative to develop, test, and pilot a new tool for local-level rural poverty assessment. The work was guided by a Sounding Board of experts from the International Fund for Agricultural Development (IFAD), other United Nations agencies, international and regional organizations, and universities around the world (see www.ifad.org/mpat). Following MPAT’s finalization and institutionalization in 2014, it was used in multiple countries including many in Sub-Saharan Africa. We conducted multiple desk-based studies with a variety of collaborators to analyze data from ~7,000 households across Eswatini, Kenya, Lesotho, Mali, Tanzania, and Zimbabwe. Because MPAT was developed based primarily on data from Bangladesh, China, India, and Mozambique, we conducted an updated assessment and evaluation of MPAT’s indicator structure and robustness based on its use in the sub-Saharan region, published in 2024. We also undertook a cross-country analyses of MPAT’s water, climate change, and health focused components and sub-components, published in 2024. [additional studies and publications are anticipated post-2026]